

- On tirzepatide, people lost 21.3% of their body weight, versus 5.3% on placebo.
- About a quarter of what they lost was lean mass, almost the same share as dieting alone.
- The drug changed how much came off, not how it came off. Strength training and enough protein are how you protect the lean part.
Am I going to lose muscle with GLP1's?
This is the question we hear most from members on, or thinking about taking, a GLP-1 such as Tirzepatide - think Mounjaro, or Zepbound. So I went looking for the best data I could find on how the category of GLP-1's affect muscle mass.
One of the clearest answers comes from a sub-study of SURMOUNT-1, a large tirzepatide trial in adults without diabetes. 160 people had DXA body-composition scans at the start and again after 72 weeks. Some took tirzepatide, some a placebo. Both groups got diet counseling aiming for a 500-calorie daily deficit and were both were told to move more, but there was no strength-training program.
What are the Surmount-1 GLP-1 study headline results?
The tirzepatide group lost 21.3% of their body weight, versus 5.3% on placebo. Fat mass fell 33.9% (versus 8.2%), and lean mass fell 10.9% (versus 2.6%). In kilograms: about 15.9 kg of fat and 5.6 kg of lean mass on tirzepatide, against 3.6 kg and 1.2 kg on placebo.
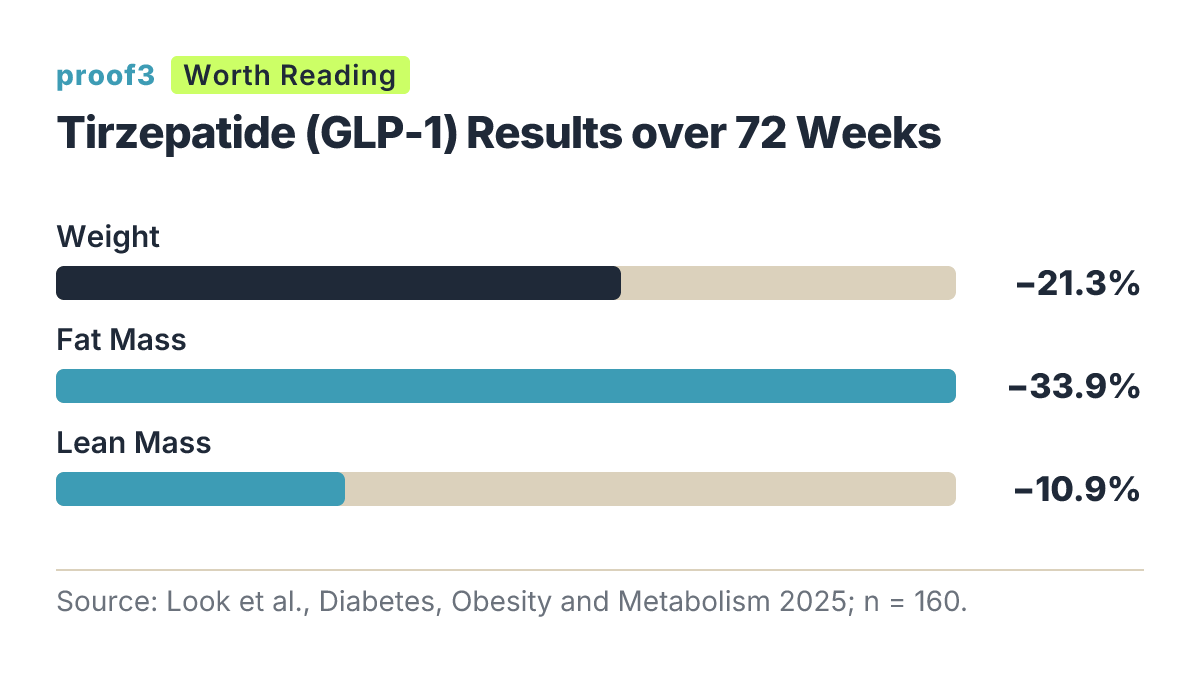
What's the difference in body composition changes of GLP-1's vs placebo?
On tirzepatide, 74% of the weight lost was fat and 26% was lean mass. On placebo (people dieting with counseling without Tirzepatide), it was 75% and 25%. The drug didn’t change how weight came off. It changed how much came off.

What the Surmount-1 study doesn't tell us about about GLP1's and muscle mass?
“Lean mass” on a DXA scan isn’t the same as muscle. It also counts water, organs and other non-fat tissue.
This sub-study measured neither strength nor physical function. Nobody in it followed a structured strength program, so we don’t know how much lifting weights would have changed the picture.
How much do we trust the Surmount-1 study on GLP-1's?
Who funded the study?
Eli Lilly, which makes tirzepatide, funded the study and was involved in its design, analysis and writing. It doesn't make it wrong, it's just a real consideration on the potential bias.
Did the outcomes and participation meet the bar?
255 people enrolled in the sub-study; 160 had both scans and were analyzed. Participants averaged 46 years old, 73% were women, and the population of participants were overweight - averaging over 200lbs - non-diabetic. So, unless there is info that we didn't initially see about why almost 100 people didn't make it to the end of the study, these characteristics make sense to us.
Body composition wasn’t one of SURMOUNT-1’s registered outcomes, so treat this as an exploratory look, not the trial’s main result, but the results seemingly show significant body composition changes
What does proof3 think of GLP-1's and muscle mass?
At proof3, we see many people on, or who've taken, GLP1's. I'd estimate 50% of them don't have a "before" body scan showing their muscle mass and bone density levels, but an interesting note is that a year ago it was 75% of people who didn't have a before scan.
The GLP-1 good news:
Many people on GLP1's, especially early-on, see weight loss and body + visceral fat, visceral fat being the fat around their organs, drop. For the substantially overweight people, in most cases it was a life-changing and likely life-extending positive outcome.
The GLP-1 challenges:
Because of people on GLP1's typically eating fewer calories, and thus fewer grams of protein, we expect they'll lose muscle mass on GLP1's.
In our experience, losing muscle and losing bone tend to travel together. It’s a big reason we push strength training.
We mainly work mostly with people over 40, many over 60. Most of them did not start with high lean muscle mass in the first place, so they're already at higher risk of bone density problems, all things equal, than a 30 year old with muscle mass already built.
In short, we follow data, and we recommend our people safely build muscle, lose body fat, lose visceral fat, and build their capabilities, all of which should be done within reasonable bounds.
How did the Surmount-1 study affect our thinking on GLP-1's?
Upon an initial read, we expected to see that people would lose muscle mass and weight + body fat. This is not a shocking forecast, and its clearly the case.
What was a very good reminder for us was that weight loss within an overweight/over-fat population is very often achieved from eating fewer calories - including less protein - while adding activity, however "easy" that activity is.
And, when you eat fewer calories, particularly when you also do not do any form of strength training, you should expect to lose muscle mass, regardless of whether you are on a GLP-1 or not.
That means we must shift our perspective. Instead of a black and white statement of "will you lose muscle mass," we really should be asking how much muscle mass you'll lose from any weight loss regiment or drug, how much different a particular regiment or drug vs the norm, and how beneficial is adding, or including, proper protein calories and strength training to your lean muscle mass maintenance vs other drugs.
In the case of Tirzepatide this study suggests you'll lose weight and body fat faster, but you will lose apx. the same percentage of muscle mass that you would have otherwise lost without the GLP-1. It just so happens that the total pounds of lean muscle lost is high because the percentage of lean muscle lost stays the same even though the weight loss is higher.
- In the case of Tirzepatide this study suggests you'll lose weight and body fat faster, but you will lose apx. the same percentage of muscle mass that you would have otherwise lost without the GLP-1.
- It just so happens that the total pounds of lean muscle lost is high because the percentage of lean muscle lost stays the same even though the weight loss is higher.
- That means that there are real tradeoffs of the importance of weight and fat loss, both for health and vanity reasons - and both matter to virtually everybody we meet - vs long term frailty and potential sarcopenia, osteopenia, and osteoporosis challenges later in life.
What do we still believe after this deeper dive?
Strength training and building muscle mass is critically important while on GLP-1's and for any weight loss journey for that matter. There is no free lunch, and if you're going to lose weight, particularly quickly, you are at higher risk for a commensurate loss of lean muscle.
What are we monitoring in the GLP-1 world to stay ahead of the muscle mass loss challenge?
[1] Trials are now testing resistance exercise and protein during GLP-1 treatment, such as LEAN-PREP (registered as NCT06885736), with primary completion listed for 2029. When those report, we’ll know whether training changes that 26% of total weight loss being lean muscle.
[2] Empirical evidence of people coming to us either on or who were on GLP-1's who are either successful or unsuccessful in maintaining, or building muscle mass. What works in the real world is always important to us.
[3] Reta, Reta, Reta...
While this article isn't about the deep science of what GLP-1's are, It's important to remember that a GLP-1 Agonists is typically used as a broad term for this category of drugs. Newer GLP-1's are actually technically much more than "1." In fact, there are single, double, and triple receptor agonists. What the heck does that mean?
- The GLP-1 Receptor (The "Satiety & Sugar Brake" Lock) - Primarily in the brain (appetite centers), the pancreas, and the stomach. Semaglutide (sold as Ozempic for type 2 diabetes and Wegovy for weight loss) is a GLP-1 drug.
- The GIP Receptor (The "Metabolic & Fat Buffer" Lock) - Heavily expressed in fat (adipose) tissue, the pancreas, and the brain. Tirzepatide (Mounjaro for diabetes, Zepbound for weight loss) acts on two receptors, GIP and GLP-1.
- The Glucagon Receptor (The "Energy Furnace" Lock) - Densely located in the liver.
New drugs coming out such as Eli Lilly's Retatrutide ("Reta") are triple receptor-agonist drugs targeting the GLP-1 receptor in the brain, the GIP receptor in the fat tissue, and glucagon in the liver.
The Reta claims, early on, are very positive about lowering body fat, but it isn't through the FDA yet, so we cannot make credible claims or have credible stances on it other than empirical successes from users.
And, if you're curious about Reta, check out this video by Dr. Kevin Joseph where he discusses the very positive, albeit very early, results of Reta on fatty liver-like disease, which is very likely where its biggest direct impact may lie.
tldr:
“It nearly erased fatty liver disease in almost nine out of 10 patients.”
— Dr. Kevin Joseph
“That 29% is the biggest weight loss ever reported for any drug in a phase 3 clinical trial ever.”
“Retatrutide isn't a weight loss drug. It's a disease fighting drug that happens to also melt fat.”

Summary on GLP-1's and succeeding on them
As we'll always do even though it's less provocative, we will always begin with "it depends,"
- Some people have side effects from GLP1's,
- Some people wanting to use GLP1's more as a maintenance drug vs a large(r) scale weight/fat loss supporter may actually have more downside risk to muscle mass and bone density loss if longer-term use of GLP1's make it harder for them to build muscle mass - this assumes they do strength training and muscle mass building program(s) in an attempt to build muscle in the first place.
- We'd like to see more data on micro-dosing GLP-1's before we take a stronger stance on that.
Our principled stance is pretty simple
When you're carrying a lot of body fat mass and visceral fat "surface area" we believe that it's typically more dangerous then losing, for ex, 1lbs of muscle mass, so we'd be in favor of doing the work - and it is, in fact, work - to lose body fat, visceral fat, and often weight (not always, though). But, within that broad statement, we want to make sure that you:
- Eat enough high-quality protein to support your muscle mass
- Don't exist on a perpetual calorie deficit - a calorie deficit is often needed to lose weight, but if you eat too little, particularly if you eat at or below your Basal Metabolic Rate ("BMR"), your body cannot sustain that forever, and we'd expect you'll burn through your muscle mass and then potentially worse the longer you stay in a deficit. And, something that often resonates well with our members is that Long, aggressive diets can slow your metabolism somewhat, which can make regain easier when calories come back up, ie if you did increase your calories you might put weight back on much more quickly.
- Strength train consistently - most of our people do 3 days per week - to give yourself the best chance to build muscle and bone density because building muscle directly supports building bone density.
- Do the lifestyle work to support your weight/fat loss and muscle gain/maintenance goals - sleep, movement, sunlight within reason, low(er) "bad" stress, purpose, relationships, and rhythm. This so often magnifies good results even though it is quietly helping in the background, if you will.
Clearly proof3 sells strength training, so you should do your homework on us before you train with us just like we're doing here, but whether you train with us or not, protect and improve your strength. Your future self, and more importantly your today self will be so happy you did.
If you’re on or considering a GLP-1, make changes with your prescribing doctor. We coach training, lifestyle, and nutrition strategies, not medication.”
Live Stronger For Longer®
Sources
- Do GLP-1 drugs cost you muscle? What one big trial actually measured — 2026
- Triple hormone receptor agonist retatrutide for metabolic dysfunction-associated steatotic liver disease: a randomized phase 2a trial — Nature Medicine
- Retatrutide Isn't a Weight Loss Drug — Here's What It Really Does (Weightloss Dr. Explains) — YouTube
- GLP-1
- Tirzepatide
- Mounjaro
- Zepbound
- SURMOUNT-1
- DXA body-composition scans
- calorie daily deficit
- Lean mass
- Eli Lilly
- Body composition
- proof3
- visceral fat
- sarcopenia
- osteopenia
- osteoporosis
- LEAN-PREP (registered as NCT06885736)
- Ozempic
- Wegovy
- Tirzepatide
- Retatrutide ("Reta")
- Dr. Kevin Joseph

